The gum around the implant bleeds when you brush.
Bleeding on probing is the earliest sign of peri-implant inflammation. It often means peri-implant mucositis — the reversible stage — and is the best time to act.

Maybe it bleeds a little when you floss. Maybe it looks puffier than the other side. Maybe a recent X-ray showed something at the implant that wasn't there before. Peri-implant disease is the leading cause of late implant failure, and the earlier it's caught, the more we can do about it. The Fotona LightWalker's combined Er:YAG and Nd:YAG protocol is one of the most studied laser-assisted approaches to managing the surface where bacteria, titanium and tissue meet.
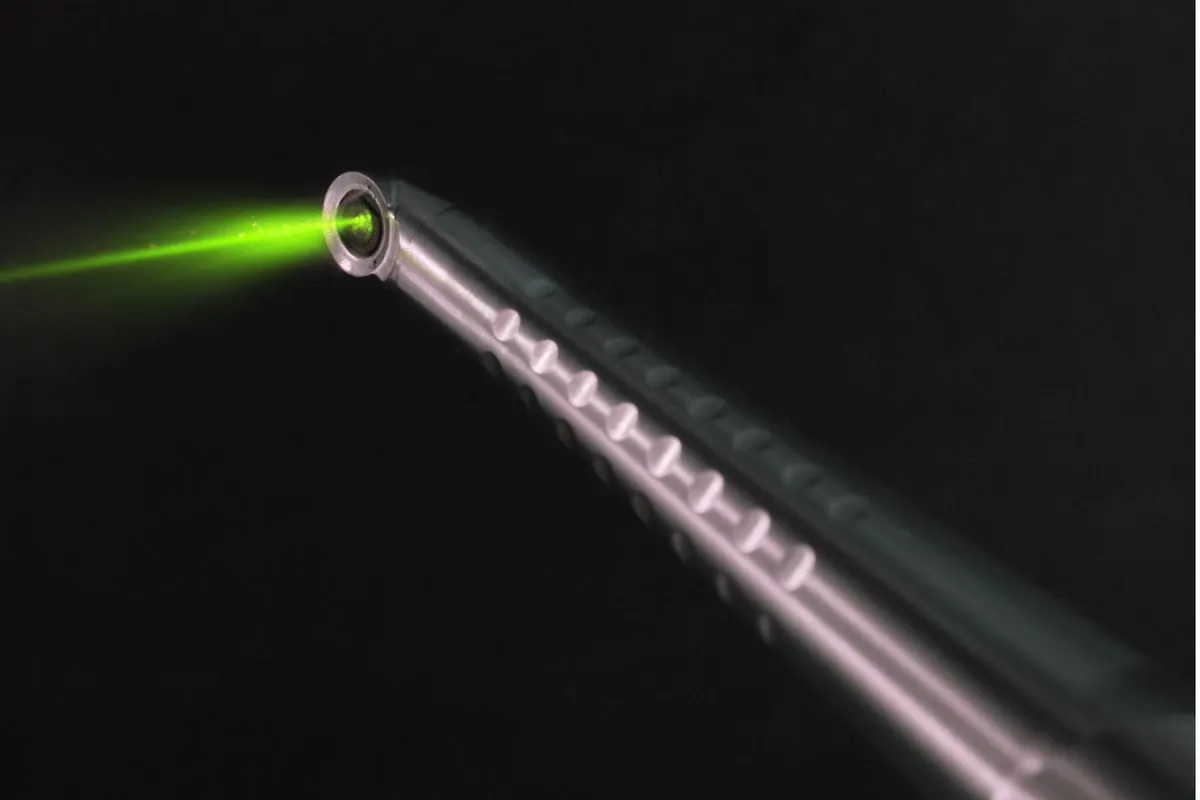 Er:YAG · 2940 nm
 Nd:YAG · 1064 nm
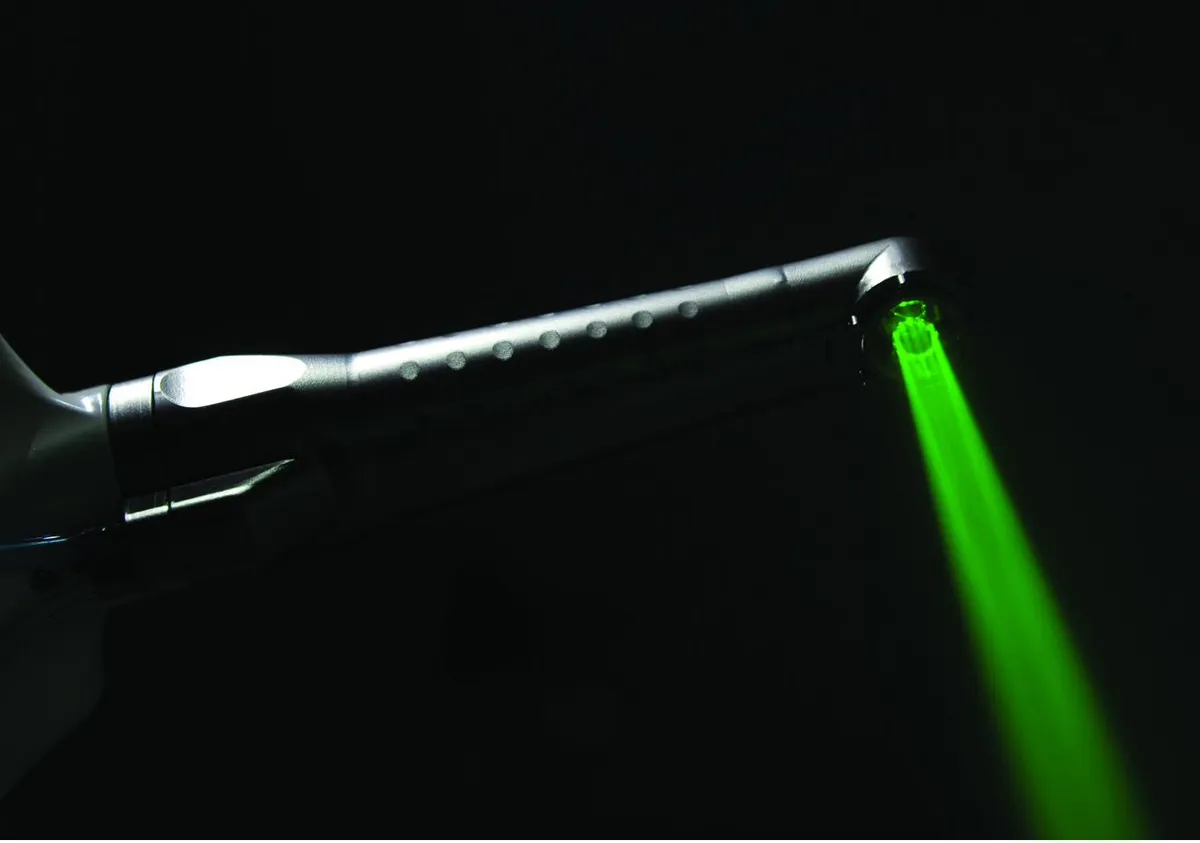 Dual-wavelength
An implant is a remarkable thing. A titanium post slowly accepted into your jawbone, holding a crown that chews and speaks and smiles like the tooth it replaced. For most patients, most of the time, it just works — sometimes for the rest of their life.
Sometimes it doesn't. The gum around it becomes inflamed. Bacterial biofilm — the same kind that causes gum disease around natural teeth — colonises the surface of the implant. Left unchecked, it begins to dissolve the supporting bone. Studies suggest somewhere between one in five and one in three implants will develop some form of peri-implant disease over their lifetime. The earlier we intervene, the more we can do.
Laser-assisted treatment matters here because the implant surface is engineered to encourage bone — the same micro-texture that makes it nearly impossible to scrape clean with conventional instruments. The Er:YAG wavelength removes inflamed tissue and biofilm without damaging titanium. The Nd:YAG wavelength disinfects more deeply. The goal is to halt the disease, settle the inflammation and stabilise the implant where it is. We will be honest with you about what is and isn't achievable for your case.
Most peri-implant disease is found early, by people who notice a small change and choose to investigate it. If any of these sound familiar, it's worth booking an assessment — even if you've been told before that everything looks fine.
Bleeding on probing is the earliest sign of peri-implant inflammation. It often means peri-implant mucositis — the reversible stage — and is the best time to act.
Subtle swelling, redness, or a gum that doesn't sit as tight to the implant crown as it once did. The tissue is telling you something is changing underneath.
Sometimes peri-implantitis is found at a routine review before you've noticed any symptoms. Catching it on imaging is often the earliest possible warning we have.
An unpleasant taste that won't shift, or a tiny amount of pus when you press on the gum, suggests established infection and warrants a prompt assessment.
A change in how the implant sits under pressure — tenderness, a sensation of mild movement, food packing where it didn't before — is worth investigating without delay.
Implants need the same ongoing maintenance as natural teeth. If it's been a while since your last review, a baseline assessment is the place to start — regardless of whether you're noticing anything.
Peri-implantitis is not a problem you can solve with a stronger antiseptic mouthwash. The bacterial biofilm sits inside the engineered micro-texture of the implant surface — the same texture that helps the implant integrate with bone. Cleaning it without damaging it is the technical challenge. The Fotona LightWalker's dual wavelengths are matched to two different parts of that job.
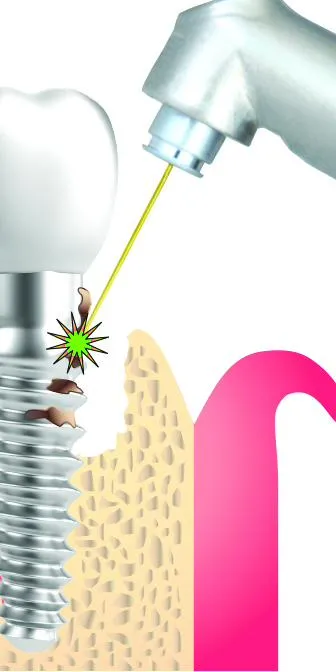 Er:YAG + Nd:YAG
Metal curettes scratch titanium. Ultrasonic tips struggle to follow the contour of the implant threads. Even plastic instruments leave biofilm behind in the micro-grooves of the surface. This is why peri-implantitis has historically been so hard to manage — the very feature that made the implant successful is what now shelters the bacteria.
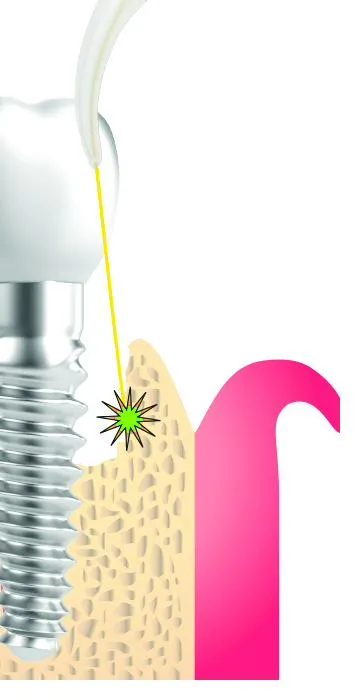
The Er:YAG wavelength (2940 nm) is strongly absorbed by water. It vaporises the water in inflamed soft tissue and bacterial biofilm but does not heat or damage titanium. It can be used to remove granulation tissue from a peri-implant bone defect, clean the implant surface itself, and gently freshen the surrounding bone — all without the mechanical contact that risks scratching the implant.
The Nd:YAG wavelength (1064 nm) penetrates further into soft tissue and is well-documented for its bactericidal effect within periodontal and peri-implant pockets. After the Er:YAG step has removed the bulk of inflamed tissue and biofilm, the Nd:YAG step deeply disinfects the pocket and the adjacent tissues — reducing the bacterial load that drives the disease.
The combined protocol is designed to halt the active disease, settle the inflammation and create the most favourable possible conditions for the surrounding tissues to stabilise. It is not a regenerative procedure. Bone that has already been lost does not reliably return. Where significant defects exist, regenerative grafting may be discussed as a separate, additional step at your specialist's discretion. We are open about the boundary between what the laser can do and what it can't.
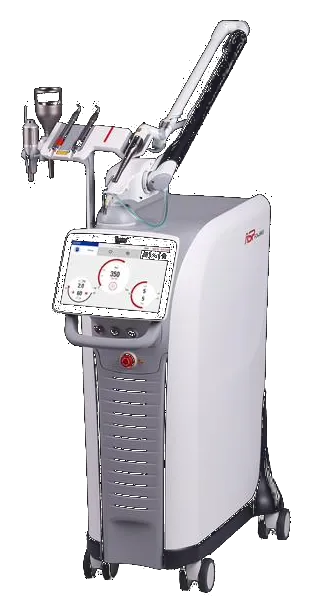 Fotona LightWalker II
The Fotona LightWalker is the only dental laser platform that combines a true Er:YAG and a true Nd:YAG source in a single unit. Most peri-implantitis laser research published in peer-reviewed journals uses this platform — because the combined protocol cannot be executed with a single-wavelength laser.
The unit is operated by a laser-trained dentist on a TGA-registered medical device. Each step of the protocol uses tightly calibrated power, pulse duration and pulse frequency, displayed on the unit's touchscreen throughout. Laser-rated eye protection is provided for you, the dentist and the assistant.
For the avoidance of doubt: peri-implant disease is a serious clinical condition that often benefits from co-management with a registered periodontal specialist, particularly in more advanced cases. Our laser-trained general dentists will be transparent at the assessment if your case is one we recommend referring or co-managing.
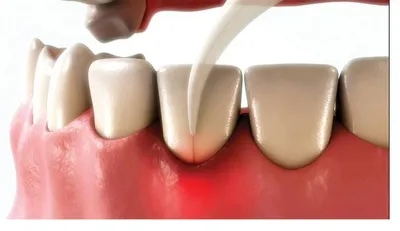
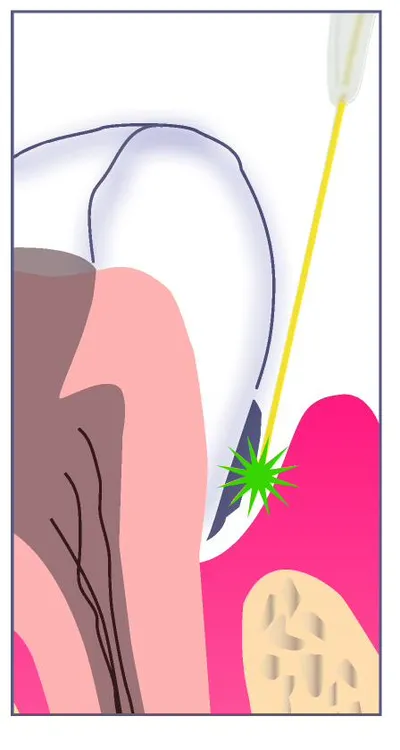
Peri-implant disease is a chronic condition. The treatment is structured across multiple visits — and the maintenance afterwards matters as much as the treatment itself.
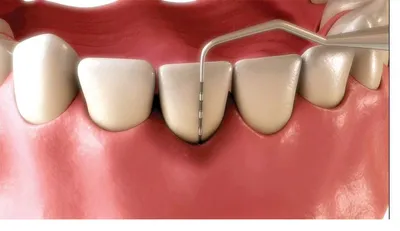
Periodontal charting around the implant, bleeding on probing, photographs, and a small targeted X-ray to establish current bone levels. The data is the starting point.
Mucositis or established peri-implantitis? How much bone has been lost? What's the most likely cause? We explain what we've found and write it down for you.
The recommended protocol, the number of visits, what each visit will involve, the maintenance schedule afterwards, the fees, and a realistic outcome range — all set out before you commit.
Local anaesthetic is used as needed for comfort. The area is isolated and a thorough mechanical clean is performed where the implant surface allows.
The Er:YAG handpiece is used to vaporise inflamed granulation tissue and biofilm from the implant surface, the pocket and the adjacent bone defect.
The Nd:YAG handpiece is used to deeply disinfect the peri-implant pocket and the surrounding tissues — reducing the bacterial reservoir that drives the disease.
Aftercare advice, interdental cleaning technique, products specific to the implant area, and an honest conversation about what daily routine the implant now needs.
Reviews at three, six and twelve months — and a long-term supportive maintenance schedule beyond that. Peri-implant disease is managed, not cured.
There's no single agreed-upon protocol for peri-implantitis — research is ongoing, and individual cases differ. The honest comparison below is what we usually walk through at the assessment.
Peri-implant disease is a slow, often quiet condition. The thing patients tell us they value most isn't a piece of equipment — it's being taken seriously, being told the truth, and being given a plan they can actually follow.
Both Er:YAG and Nd:YAG used together, on the platform the protocol was developed for. The combination is what makes the approach distinctive — not either wavelength alone.
We will tell you whether your implant has mucositis or established peri-implantitis, how much bone has been lost, and what we realistically think the treatment will achieve. No softening of the facts.
Advanced cases often benefit from periodontal specialist input. We refer or co-manage where appropriate and will say so at the assessment. We don't keep cases beyond what we can do well.
The treatment visit matters, but the structured supportive care that follows is what determines the long-term outcome. We build a maintenance schedule that fits your life, not the other way around.
Probing depths, bleeding scores, photographs, X-rays — recorded, dated and explained. You can see the change visit-by-visit, and so can any other practitioner you ever see for it.
We manage peri-implant disease around implants placed at any practice, using any system, in any country. We don't ask whose implant it was — we just need to help you keep it.
Most patients come in with a mix of worry, frustration and uncertainty. The questions below are the ones that come up again and again. If yours isn't here, please raise it at the assessment.
Peri-implantitis is inflammation around a dental implant that has progressed to involve loss of the supporting bone. Its earlier, reversible stage — inflammation of the gum tissue around the implant without bone loss — is called peri-implant mucositis.
Both are driven by bacterial biofilm accumulating on the implant surface, often combined with risk factors like smoking, uncontrolled diabetes, or excessive bite forces on the implant. The distinction between mucositis and peri-implantitis matters because the management approach and the prognosis differ. The earlier we catch and address inflammation, the more we can do about it.
The early signs are often subtle: gum around the implant that bleeds when you brush or floss, mild swelling or redness, occasional tenderness, or a change in how the gum looks compared with your other teeth.
As things progress you might notice a small amount of pus, persistent bad taste, deepening of the gum pocket around the implant, or — in late stages — the implant feeling different to bite on. Many cases are first picked up on a routine X-ray before there are noticeable symptoms. A clinical examination and a small targeted X-ray are how we confirm what's happening underneath.
An implant surface is engineered to encourage bone to grow into it — that same texture makes it very hard to clean once bacterial biofilm has colonised it.
Traditional metal instruments scratch titanium. Plastic instruments are limited by their geometry. Ultrasonic tips struggle to follow the threads of the implant. The Er:YAG wavelength is effective at removing soft tissue and biofilm from titanium without harming the surface. The Nd:YAG wavelength then penetrates further to disinfect the surrounding tissues. Used together, the combination is one of the most studied approaches to implant surface decontamination in the peer-reviewed literature.
The goal of treatment is to halt the disease process, settle the inflammation, and give the surrounding tissues the best chance of stabilising at their current level.
The outcome depends on how much bone has already been lost, the location of the implant, your general health, smoking status, control of any underlying conditions like diabetes, and how consistently you can maintain the area afterwards. Lost bone does not reliably regenerate. We will give you an honest, individualised read on what we think is achievable at your assessment, and we will not over-promise. Where the case is too advanced for a predictable outcome, we will say so.
We use local anaesthetic where useful to keep you comfortable throughout the appointment. Most patients describe the laser-assisted approach as gentler than the alternative — open-flap mechanical debridement — because the inflamed tissues can often be addressed without scalpel surgery in early-to-moderate cases.
Some tenderness for a day or two afterwards is normal and is usually well-managed with simple analgesics. We'll give you clear written aftercare guidance, including what to look out for and when to call us.
Plan for at least an initial assessment visit, one to two treatment visits depending on the severity of the case, and a structured series of review appointments — typically at three, six and twelve months.
Peri-implant disease is a chronic condition that requires ongoing maintenance, not a one-off fix. After the first year of structured reviews, we move you onto an individualised long-term supportive maintenance schedule. We will set out the full plan for you in writing after the assessment so you know exactly what to expect.
Sometimes the most honest assessment is that an implant has lost too much supporting bone — or is mobile — and trying to treat it would only delay an outcome that is going to happen anyway. In that case we will say so plainly.
We'll talk you through what removal would involve, the healing period that follows, and whether replacement is realistic — either with a new implant after a period of healing and any necessary grafting, or with an alternative restoration such as a bridge or partial denture. The decision is always yours, and we will support whichever path you choose.
Ongoing professional maintenance is the single most important factor. We typically recommend a structured peri-implant cleaning visit every three to four months in the first year after treatment, then individualised based on how the area is responding.
Daily home care around the implant is the other half — we'll teach you the technique and the products that work for your specific implant. Controlling risk factors like smoking, uncontrolled diabetes and excessive grinding, along with addressing any bite forces falling on the implant, are also part of a complete plan. Most recurrent peri-implant disease comes down to maintenance falling away, so the plan we build with you is one you can actually follow.
Not at all. We manage peri-implant disease around implants placed at any practice — including older systems, implants placed elsewhere in Australia, and implants placed overseas.
We will ask for any records or imaging you can provide, but if you don't have them, we'll take new baseline records as part of the assessment. There is no judgement and no preference for our own work — what matters is helping you keep the implant you've got.
Yes — laser-assisted peri-implantitis management is offered across all three Magical Smiles clinics: Caroline Springs, Bacchus Marsh and Point Cook.
Our team helps coordinate the appointment, the records transfer if relevant, and the long-term review schedule afterwards. The same dentist will usually see you across the treatment and review visits, for continuity.
Laser-assisted peri-implantitis management is offered across all three Magical Smiles clinics — Caroline Springs, Bacchus Marsh and Point Cook. Whichever feels closest to home or work, our team will help arrange a time that suits.
Burnside · Taylors Hill · Caroline Springs
Maddingley · Darley
Wyndham · Sanctuary Lakes
The Fotona LightWalker is used across a range of treatments — each tuned to a different tissue and a different clinical goal.

If something around your implant has changed — even subtly — the assessment is where we work out what it is and what to do about it. Early intervention is, by some distance, the most powerful tool we have in this whole conversation. No pressure to commit to anything at the consultation; we'd just rather know now than later.